Retatrutide for sleep apnea
Two NEJM phase 3 trials just put a triple-agonist weight-loss drug on the OSA map - with clear AHI drops versus placebo over 80 weeks. Here is what TRIUMPH-1-OSA and TRIUMPH-2-OSA actually showed, how retatrutide differs from already-approved tirzepatide (Zepbound), and what still matters for residual snoring.


Quick answer
Retatrutide lowered breathing-event rates more than placebo in two large phase 3 OSA trials published in the New England Journal of Medicine in October 2026. In people without diabetes, the 9 mg and 12 mg doses cut average AHI by roughly 32-34 events per hour versus about 10 on placebo over 80 weeks (placebo-adjusted differences about 22-24 events/hour). People with type 2 diabetes also improved more than placebo, with somewhat smaller absolute gaps. Weight fell substantially on active drug.
Retatrutide is still investigational. Tirzepatide (Zepbound) is the incretin that already carries a U.S. FDA label for moderate-to-severe OSA with obesity. Neither drug replaces a sleep diagnosis, and neither rebuilds soft-palate tone by itself. If nights stay loud after weight change, train the residual vibration path and keep prescribed airway therapy until a clinician restudies you.
How weight-loss medicines can change sleep apnea
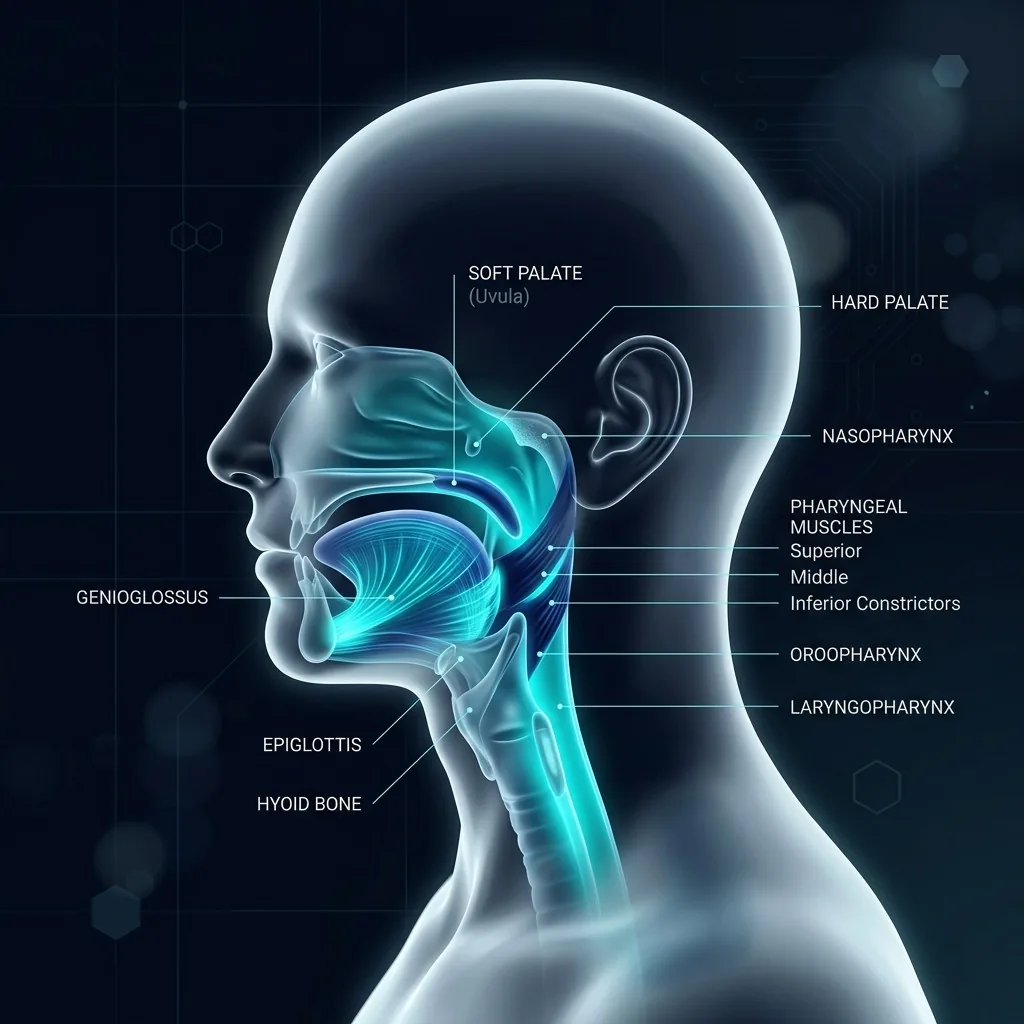
Obstructive sleep apnea is repeated upper-airway narrowing or collapse during sleep. Extra soft tissue is one of the most common amplifiers: fat pads at the tongue base and soft palate shrink the lumen, and central body mass can change chest mechanics. Sleep clinicians have long said that losing about 10-20% of body weight can meaningfully improve AHI for many people with obesity-linked OSA - and that sticking the landing with diet alone is hard.
That is why incretin medicines entered the OSA conversation. Tirzepatide pairs GIP and GLP-1 receptor activity. Retatrutide adds glucagon-receptor activity as a triple agonist. In OSA trials, the clinical bet is mostly mechanical and metabolic: less tissue bulk and lower weight should reduce collapse frequency, with possible secondary gains in symptoms and cardiometabolic markers. These are not hypoglossal nerve stimulators and not CPAP masks.
Fat pads shrink the airway
Weight can crowd the throatExtra soft tissue around the tongue base, soft palate, and pharyngeal sidewalls narrows the path air must travel. Sleep surgeons and obesity-sleep clinicians describe this as one of the most common reversible amplifiers of snoring and OSA when BMI is high.
Chest and belly load the airway
Body mass changes breathing mechanicsCentral adiposity can reduce how easily the chest expands and how the diaphragm moves. That raises the work of breathing and can worsen collapse even when the nose is clear. Weight loss can improve mechanics without fixing every anatomic bottleneck.
Incretin drugs mainly work through weight (and related pathways)
Drug effect rides the weight curveTirzepatide (dual GIP/GLP-1) and investigational retatrutide (triple GIP/GLP-1/glucagon) are studied as once-weekly injections that produce large average weight reductions. OSA trial benefits track with that weight change. They are not tongue-protrusion implants or CPAP machines.
Tone and anatomy still matter
Weight loss is not a universal snore curePeople with normal BMI still snore and develop OSA when jaws, tonsils, nasal blockage, or floppy palate tissue dominate. ENT framing stresses residual vibration after weight change. Airway muscle training targets that residual mechanical load.
What the 2026 TRIUMPH-OSA trials showed
In October 2026, NEJM published retatrutide results for OSA nested inside larger phase 3 obesity programs (TRIUMPH-1 and TRIUMPH-2). Adults with moderate-to-severe OSA and BMI of at least 27 were randomized to once-weekly retatrutide 4 mg, 9 mg, or 12 mg or placebo for 80 weeks. One trial excluded type 2 diabetes (TRIUMPH-1-OSA, n=243). The other enrolled people with type 2 diabetes (TRIUMPH-2-OSA, n=448). Primary end point: change in AHI.
| Cohort | 4 mg | 9 mg | 12 mg | Placebo |
|---|---|---|---|---|
| TRIUMPH-1-OSA (no T2D) mean AHI change | -22.9 | -34.3 | -31.7 | -9.9 |
| vs placebo (difference) | -13.0 | -24.4 | -21.9 | - |
| TRIUMPH-2-OSA (with T2D) mean AHI change | -19.2 | -24.7 | -25.4 | -10.3 |
| vs placebo (difference) | -8.9 | -14.4 | -15.1 | - |
Values are mean AHI changes in events per hour at 80 weeks using the hybrid-treatment estimand reported in the NEJM abstract (doi 10.1056/NEJMoa2611477). Confidence intervals and ITT estimands are in the full paper. This table is educational paraphrase, not a substitute for the primary publication.
Weight loss was large on active drug (roughly 12-22% mean body-weight reduction across retatrutide doses in TRIUMPH-1-OSA versus about 5% on placebo in the abstract summary). Gastrointestinal adverse events were the most common safety signal - the same class pattern patients already hear about with dual agonists.
Context from the prior standard: our 2026 treatment landscape page covers tirzepatide/Zepbound after SURMOUNT-OSA and the December 2024 FDA OSA approval. Retatrutide is the next investigational step in that same weight-first drug lane, not a replacement for CPAP counseling or for non-weight OSA phenotypes.
Who these results apply to
Who these OSA drug trials enrolled
- Adults with moderate-to-severe OSA (AHI typically 15+ events/hour on study definitions)
- BMI at least 27 (retatrutide TRIUMPH-OSA) or obesity criteria matching the SURMOUNT-OSA program for tirzepatide
- People unable/unwilling to use PAP, or who stopped PAP for the trial window in nested designs
- Separate cohorts with and without type 2 diabetes in the retatrutide OSA pair
Who is less likely to see a "cure" from weight-loss drugs alone
- Primary snoring or OSA driven mainly by jaw structure, large tonsils, or fixed nasal blockage
- Normal-weight snorers without a fat-pad phenotype
- Anyone expecting a weekend fix without clinician follow-up or a sleep diagnosis
- People who need immediate airway support for severe oxygen desaturations while waiting months for weight change
See a clinician first if...
- Gasping, choking, witnessed pauses, or severe daytime sleepiness
- You are already on CPAP, an oral appliance, or oxygen and want to change therapy
- History of pancreatitis, medullary thyroid cancer risk factors, or other GLP-1 class cautions your clinician tracks
- Unintentional weight loss, chest pain, or other red-flag symptoms unrelated to elective weight therapy
Practical next steps
Get a real OSA diagnosis before chasing a drug headline
Trial enrollment required documented moderate-to-severe OSA. A partner video of snoring is not a sleep study. Use screening tools as a conversation starter, then pursue home or lab testing when indicated.
Treat retatrutide as investigational (as of Oct 2026 publication)
NEJM phase 3 OSA data are strong signals, not a pharmacy shelf product. Tirzepatide/Zepbound already has an FDA OSA-with-obesity label. Do not compound, import, or self-dose research peptides based on a trial abstract.
Plan for months, not nights
TRIUMPH-OSA followed people for 80 weeks. SURMOUNT-OSA ran 52 weeks. Expect gradual AHI and weight change under medical supervision, with GI side effects as the most common trade-off in the published programs.
Keep a residual-snoring plan
Even when AHI improves, soft-palate vibration, nasal blockage, alcohol timing, back sleep, and weak airway tone can keep nights loud. Positional habits, nasal care, prescribed PAP/oral appliances when indicated, and oropharyngeal training cover different residual pieces.
This page is educational, not prescribing advice. Weight-loss medicines require a licensed clinician, ongoing monitoring, and a plan for what happens to CPAP or oral appliances as AHI changes. Do not stop prescribed therapy because a trial abstract looks encouraging.
Expert videos on incretins, weight, and OSA
Clinician framing and demonstration context only. Clinical claims on this page are grounded in the Sources list, not in video captions. Retatrutide-specific OSA clips are still sparse right after the NEJM drop, so we pair TRIUMPH explainers with tirzepatide/Zepbound clinician guides and ENT weight-and-snoring context.
Med Journal Club - plain walkthrough of TRIUMPH-1 design, triple-agonist framing (GIP/GLP-1/glucagon), and how the nested OSA basket sits beside weight and knee-pain end points.
NEJM Group - short official summary of the SURMOUNT-OSA tirzepatide program that set the modern incretin-OSA benchmark before retatrutide.
IntraBalance / Dr. Audrey Wells (sleep + obesity medicine) - who responds when soft-tissue bulk is the disease driver, BMI and diagnosis gates, dual-agonist basics, and why weight is often a factor but not always the only factor.
Vik Veer, NHS ENT surgeon - the two common myths (OSA only happens if you are overweight; weight loss always cures snoring), scatter of BMI vs AHI, and residual soft-palate vibration after weight change.
Dr. Jordan Weiner (ENT / sleep surgery) - fat deposits in tongue base, soft palate, and sidewalls; abdominal load on breathing mechanics; how surgeons counsel weight loss beside CPAP and procedures.
When airway exercises still help
Weight-loss medicines change bulk and metabolism. They do not automatically teach the soft palate and tongue to hold tone at 3 a.m. If vibration remains after BMI drops - or while you wait months for drug effect - oropharyngeal training is the residual mechanical lever.
Randomized trials of oropharyngeal programs reduced snoring metrics (Ieto 2015) and improved OSA outcomes versus sham (Guimaraes 2009). A myofunctional therapy meta-analysis (Camacho 2015) found pooled reductions in snoring and apnea-hypopnea index in selected populations. Those results support a daily airway routine as an adjunct - not as a substitute for OSA diagnosis, PAP when indicated, or clinician-managed weight therapy.
A practical stack for many people with obesity-linked OSA and residual snoring: STOP-BANG screen, sleep testing when scores or symptoms warrant it, prescribed PAP or oral appliance adherence while weight changes, side-sleep habits, alcohol timing, and a guided tongue/palate/throat routine. Related guides: soft-palate drills, tongue exercises, and oropharyngeal exercise studies.
Airway Trainer turns those drills into a short daily session so residual vibration work is not only willpower and random YouTube tabs while a weight plan runs in parallel.
When to see a doctor first
A news cycle about an investigational drug is not a care plan. Get evaluated - do not only screenshot a trial table - if you have:
- Gasping, choking, witnessed pauses, or severe daytime sleepiness
- Drowsy driving or work impairment from sleepiness
- Existing CPAP, oral appliance, oxygen, or bariatric plans you want to change
- History that complicates incretin therapy (discuss class cautions with your clinician)
CPAP, oral appliances, hypoglossal nerve stimulation, positional therapy, nasal surgery, weight management (including labeled tirzepatide when appropriate), and airway exercises each solve different pieces. Match the tool to the cause after a real assessment.
Sources
- Grunstein RR, et al. N Engl J Med. 2026. Retatrutide once weekly for treatment of obstructive sleep apnea. doi: 10.1056/NEJMoa2611477. ClinicalTrials.gov NCT05929066, NCT05929079.
Two phase 3, double-blind, placebo-controlled trials nested in larger retatrutide basket studies: TRIUMPH-1-OSA (n=243, no type 2 diabetes) and TRIUMPH-2-OSA (n=448, with type 2 diabetes). Adults with moderate-to-severe OSA and BMI at least 27 received once-weekly retatrutide 4, 9, or 12 mg or placebo for 80 weeks. Primary end point: change in apnea-hypopnea index (AHI). At 80 weeks (hybrid-treatment estimand), TRIUMPH-1-OSA mean AHI changes were -22.9 (4 mg), -34.3 (9 mg), and -31.7 (12 mg) vs -9.9 placebo (differences vs placebo -13.0, -24.4, and -21.9 events/hour). TRIUMPH-2-OSA changes were -19.2, -24.7, and -25.4 vs -10.3 placebo (differences -8.9, -14.4, and -15.1). Weight loss was a key secondary end point. Most common adverse events were gastrointestinal. Investigational product; not an FDA approval decision. - Malhotra A, et al. N Engl J Med. 2024;391:1193-1205. Tirzepatide for the treatment of obstructive sleep apnea and obesity. doi: 10.1056/NEJMoa2404881. PMID: 38912654.
SURMOUNT-OSA phase 3 program: once-weekly tirzepatide vs placebo in adults with moderate-to-severe OSA and obesity, with and without positive airway pressure pathways. Tirzepatide produced larger AHI reductions and substantial body-weight loss versus placebo over 52 weeks, establishing the first large incretin OSA evidence base that retatrutide trials build on. - U.S. Food and Drug Administration / Eli Lilly. FDA approves Zepbound (tirzepatide) for moderate-to-severe obstructive sleep apnea in adults with obesity. December 2024.
Regulatory milestone: tirzepatide (Zepbound) became the first prescription medicine FDA-approved specifically for moderate-to-severe OSA in adults with obesity, used with a reduced-calorie diet and increased physical activity. This is a separate product and label from investigational retatrutide. - Mayo Clinic. Obstructive sleep apnea: Diagnosis and treatment.
Patient-facing overview of OSA evaluation and treatment options (CPAP, oral appliances, lifestyle, surgery) and why weight is a major but not universal driver of airway collapse. - Mayo Clinic. Snoring: Diagnosis and treatment.
Clinical snoring overview: lifestyle factors, when snoring warrants apnea evaluation, and that anatomy and muscle tone still matter after weight change. - Ieto V, et al. Chest. 2015 Sep;148(3):683-691. PMID: 25950418.
Randomized trial: oropharyngeal (airway) exercises reduced snoring frequency and snoring power in habitual snorers - a non-drug path to lower vibration load when tone is part of the problem. - Guimaraes KC, et al. Am J Respir Crit Care Med. 2009 May 15;179(10):962-968. PMID: 19234106.
Randomized trial: daily upper-airway exercises improved obstructive sleep apnea severity and snoring versus sham control. - Camacho M, et al. Sleep. 2015 May 1;38(5):669-675. PMID: 25348130.
Meta-analysis of myofunctional therapy for OSA: pooled trials show meaningful reductions in snoring and apnea-hypopnea index in selected populations.
Retatrutide and sleep apnea: FAQs
What is retatrutide and how is it different from Zepbound?
Retatrutide is an investigational once-weekly injection that activates three hormone pathways: GIP, GLP-1, and glucagon (a triple agonist). Zepbound is tirzepatide, a dual GIP/GLP-1 agonist that already has FDA approval for obesity and, separately, for moderate-to-severe OSA in adults with obesity. Retatrutide is not interchangeable with tirzepatide on a pharmacy counter as of the October 2026 NEJM publications.
Does retatrutide cure sleep apnea?
No medication in these programs is framed as a universal cure. In TRIUMPH-1-OSA and TRIUMPH-2-OSA, higher doses of retatrutide lowered average AHI more than placebo over 80 weeks, and more participants reached milder disease categories in secondary analyses reported in coverage of the trials. Individual response still varies, GI adverse events are common, and anatomy-driven OSA can remain after weight loss.
How much did AHI fall in the retatrutide OSA trials?
Using the hybrid-treatment estimand at 80 weeks: without diabetes (TRIUMPH-1-OSA), mean AHI changes were about -22.9, -34.3, and -31.7 events/hour on 4, 9, and 12 mg versus -9.9 on placebo (placebo-adjusted differences about -13.0, -24.4, and -21.9). With type 2 diabetes (TRIUMPH-2-OSA), changes were about -19.2, -24.7, and -25.4 versus -10.3 on placebo (differences about -8.9, -14.4, and -15.1). Always read the full paper for estimands, confidence intervals, and safety.
Is tirzepatide (Zepbound) already approved for sleep apnea?
Yes. In December 2024 the FDA approved Zepbound (tirzepatide) for moderate-to-severe obstructive sleep apnea in adults with obesity, used with diet and activity changes. That approval rests on the SURMOUNT-OSA program published in NEJM. It is the current labeled incretin option in the United States; retatrutide remains investigational for OSA despite phase 3 data.
Will losing weight always stop snoring?
Often it helps when fat pads and chest/belly load are major drivers, but it is not guaranteed. ENT surgeons emphasize that people at many BMIs snore, and floppy soft-palate tissue, nasal blockage, alcohol, and sleep position can keep vibration going after weight change. Treat weight loss as one lever inside a multi-factor plan.
Do I still need CPAP if I start a weight-loss medicine?
Many people should keep prescribed airway therapy until a clinician restudies breathing after meaningful weight change. CPAP remains first-line for many moderate-to-severe OSA phenotypes. Drug trials carefully define PAP use, washout, and inclusion rules; real-world decisions belong with your sleep clinician, not a blog post.
Can airway exercises help while weight is changing?
Yes as an adjunct for the muscle-tone half of snoring. Randomized oropharyngeal programs (Ieto 2015, Guimaraes 2009) and a myofunctional therapy meta-analysis (Camacho 2015) support lower snoring load and, in selected groups, better AHI. Exercises do not replace OSA diagnosis, PAP when indicated, or clinician-managed weight therapy.
Weight drugs change bulk. Tone still needs reps.
Follow clinician-led OSA and weight care when you qualify. Airway Trainer handles the daily tongue, palate, and throat work that lowers residual snoring vibration - the piece an injection cannot train for you.
Related reading: New sleep apnea treatments 2026 · Snoring and vascular aging · CPAP 4-hour rule