GERD and snoring
Acid reflux and loud snoring often share the same night - and sometimes the same loop. Here is how GERD and silent throat reflux (LPR) connect to airway collapse, what meta-analyses show, how CPAP can change reflux burden, and when airway muscle training still matters.


Quick answer
Yes - GERD, silent throat reflux, snoring, and obstructive sleep apnea often reinforce each other. Pooled studies find people with GERD have higher odds of OSA and vice versa. Laryngopharyngeal reflux shows up in roughly 45% of OSA patients in one meta-analysis. Nighttime acid or pepsin in the throat can swell soft tissue; apnea-related negative pressure can pull more reflux upward.
Fix both sides when both are present: reflux lifestyle and medical care when indicated, sleep testing when apnea red flags appear, and airway-tone work for the vibration/collapse half. Treating only heartburn or only a snore gadget often leaves the loop running.
How GERD and snoring feed each other
Classic GERD is stomach contents moving back into the esophagus when the lower esophageal sphincter fails to keep a seal. Mayo Clinic notes frequent reflux can irritate the esophagus and that nighttime reflux may bring cough, laryngitis, and asthma-like symptoms - not only chest burn.
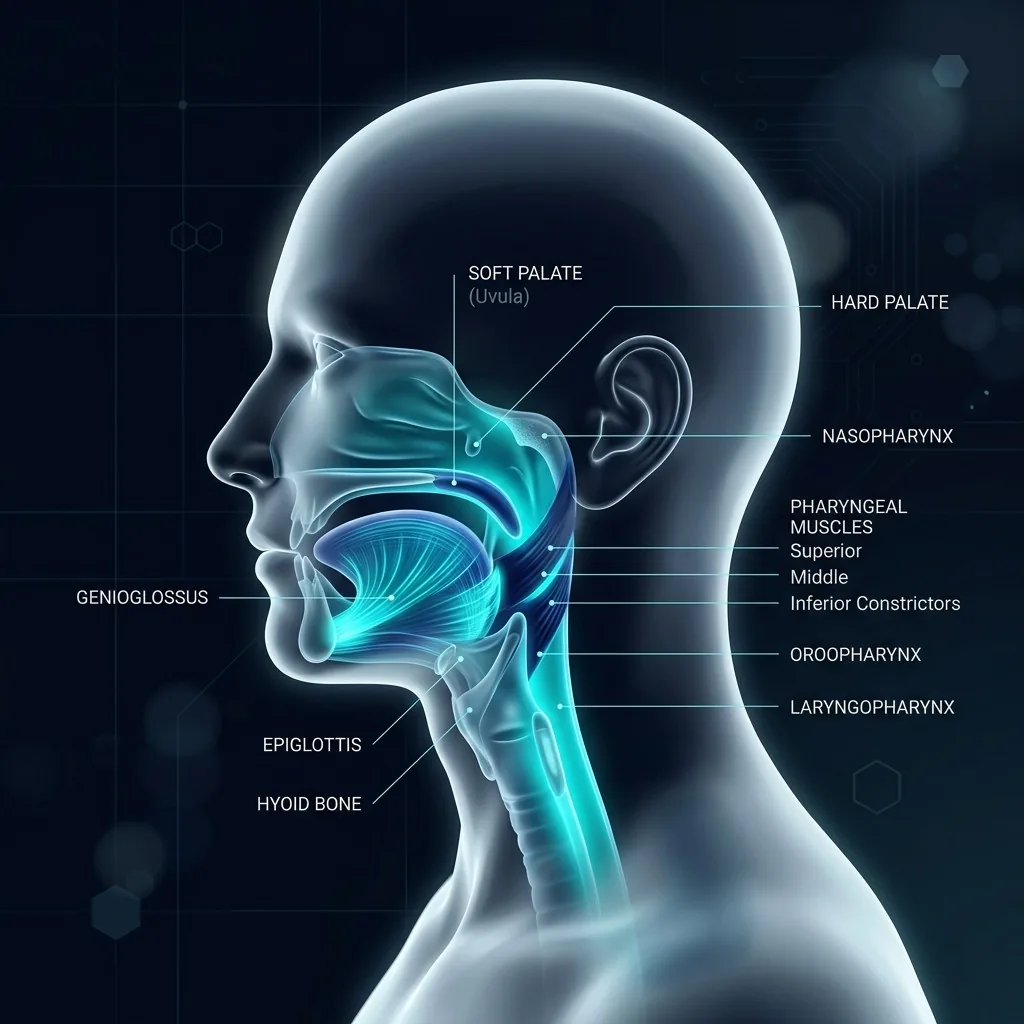
When material reaches the throat and larynx, clinicians call it laryngopharyngeal reflux (LPR) or silent reflux. ENT educators emphasize that many patients never feel heartburn. They show up with throat clearing, hoarseness, cough, mucus, ear pressure, or a lump sensation - and an airway that looks irritated on scope. Swelling at the tongue base, tonsils, and nose stacks collapse risk on top of whatever anatomy you already had.
From the sleep side, obstructive events turn the chest into a suction pump. Clinicians demo the idea with a pinched-nose inhale: repeated negative pressure overnight can favor reflux even while you sleep through it. Partners hear the snore; you may only notice a raw throat at breakfast and blame the coffee.
OSA can pull reflux upward
Negative-pressure vacuum from airway collapse
When the upper airway collapses, the chest generates strong negative pressure as you try to inhale against a blocked path. Sleep clinicians describe that vacuum as a force that can favor stomach contents moving up the esophagus - even if you never feel classic daytime heartburn.
Silent reflux can crowd the airway
Laryngopharyngeal reflux (LPR) and throat swelling
Reflux that reaches the throat and voice box can irritate delicate mucosa. ENT framing emphasizes tongue-base and tonsil swelling, nasal congestion, throat mucus, and inflammation stacked on an already narrow sleep airway - a mechanical snoring amplifier, not just a GI complaint.
Same bed, same triggers
Shared nighttime setup
Lying flat, late large meals, alcohol, fatty foods, and back sleep worsen both reflux exposure and airway collapse for many people. Mayo Clinic lists late meals, alcohol, and nighttime heartburn patterns among GERD drivers; the same stack shows up in snoring guides.
CPAP can cut reflux burden
Treating the apnea side
A meta-analysis of CPAP in OSA patients with reflux measures found fewer and shorter reflux events and better symptom scores after positive-pressure therapy. That does not prove every snorer needs CPAP - it supports the bidirectional physiology story when OSA is confirmed.
What the studies show
Association data are consistent enough to take seriously. A 2023 systematic review and meta-analysis in the Journal of Gastroenterology and Hepatology (El Hage Chehade and colleagues; PMID 37300443) pooled six studies with 2,950 patients and found a significant GERD-OSA link (OR 1.53, 95% CI 1.23-1.91). The signal held across different diagnostic tools and after sensitivity analyses for gender, BMI, smoking, and alcohol. GERD did not clearly change OSA severity scores in that pool - comorbidity, not a simple dose ladder.
An earlier Sleep and Breathing meta-analysis (Wu and colleagues; PMID 29987514) of seven articles (2,699 patients) reported a pooled OR of about 1.75 (95% CI 1.18-2.59) between OSAHS and GERD under a random-effects model.
On the throat-specific side, Magliulo and colleagues (2018; PMID 30224217) meta-analyzed LPR in OSA and found LPR in about 45.2% of 870 identified OSA patients. AHI did not differ significantly by LPR status; BMI was higher among LPR-positive patients. That matches the clinic pattern: lots of silent throat reflux in apnea clinics, not a one-to-one severity curve.
Treatment direction matters too. A meta-analysis of CPAP effects on reflux in OSA (Li and colleagues, Sleep and Breathing) associated positive-pressure therapy with fewer reflux events, less acid exposure time, lower DeMeester scores, and better reflux symptom scores, with clearer gains when therapy ran longer. Separately, a 2024 PeerJ meta-analysis (Tan and colleagues; PMID 38646475) supports a bidirectional relationship between sleep problems and GERD more broadly - insomnia and short sleep raise GERD odds, and GERD raises odds of poor sleep quality.
Bottom line: the "reflux and snoring are unrelated" story is the weak one. Causation is still multi-factorial, study tools differ, and not every heartburn patient has apnea. The practical read is still clear - screen both directions when nights are loud and the throat is angry.
Who should think about GERD and snoring together
Why this page matters if you snore and have reflux
- Heartburn, regurgitation, or sour taste at night plus loud snoring
- Morning raw throat, chronic throat clearing, hoarseness, or cough without much daytime heartburn (LPR pattern)
- Partners report snoring plus choking or gasping
- You only treated one side (PPI stack or snore gadget) and nights stayed loud
Where the comorbidity signal is strongest
- Known or suspected obstructive sleep apnea
- Higher BMI phenotypes (LPR+ OSA cohorts often skew heavier)
- Hiatal hernia, late-night eating, or heavy evening alcohol
- Back sleep with both reflux and snoring on the same nights
See a clinician first if...
- Gasping, choking, or witnessed pauses in breathing
- Severe daytime sleepiness, drowsy driving, or work impairment
- Chest pain, trouble swallowing, unintentional weight loss, or vomiting blood
- Heartburn medicines more than twice a week without a plan, or red-flag GI symptoms
Practical next steps for reflux-linked snoring
Screen both problems, do not pick one specialty only
Throat-only symptoms can be LPR; loud snoring can be OSA. ENT, GI, and sleep medicine often each see a slice. If you have apnea red flags, pursue a sleep evaluation rather than only escalating antacids. If you have GERD red flags, see a clinician rather than only downloading a snore app.
Fix the shared nighttime stack
Finish large meals 2-3 hours before bed when you can. Limit late alcohol. Prefer side sleep (many clinicians prefer left side when reflux is active). Elevate the head of the bed with blocks or a wedge designed for torso lift, not only an extra pillow that flexes the neck.
Treat confirmed OSA seriously
If a study shows obstructive sleep apnea, adherence to prescribed therapy (CPAP, oral appliance, positional therapy as indicated) can improve breathing and, in pooled data, reflux event burden. Skipping OSA care while chasing only heartburn often leaves the loop intact.
Train airway tone on the days between bad nights
Reflux care does not rebuild soft-palate and tongue tone. Oropharyngeal and myofunctional programs target the vibration and collapse side. Trials support snoring and selected OSA improvements; they are adjuncts, not a DIY cure for GERD or severe apnea.
This page is educational, not a diagnosis or treatment plan. Chest pain can be cardiac. Nighttime choking can be apnea, reflux, asthma, or other problems. Match tools to a real assessment when red flags are present.
Expert videos on reflux, LPR, and sleep breathing
Clinician framing and demonstration context only. Clinical claims on this page are grounded in the Sources list, not in video captions.
ENT Specialists - how silent reflux can swell tongue base, tonsils, residual adenoids, and nasal tissue, why scopes look for reflux changes in adult OSA, and the bidirectional loop when apnea favors more reflux.
Sleep Medicine Institute of Texas - nighttime reflux timing, negative intrathoracic pressure as a vacuum, why morning burn can reflect overnight events, and why OSA evaluation belongs in the plan.
NJ ENT (We Nose Noses) - LPR symptom pattern (cough, throat clearing, hoarseness) without chest burn, post-meal and lying-down timing cues, and why patients often present to ENT first.
Melbourne ENT Group - GORD vs LPR mechanisms, lifestyle foundations (meal timing, bed elevation, trigger foods), and why PPIs help esophageal symptoms more reliably than isolated LPR.
Dr. Matthew Glover (GI) - patient-facing walkthrough of LPR as an airway irritant, the 2023 GERD-OSA association paper, CPAP-and-reflux meta-analysis framing, and why heartburn-only care can miss snoring/OSA.
When airway exercises still help
Reflux care changes chemistry, meal timing, and sphincter stress. It does not automatically rebuild soft-palate and tongue endurance. If vibration and collapse remain after you clean up late meals and alcohol, tone work is the other half.
Randomized trials of oropharyngeal programs reduced snoring metrics (Ieto 2015) and improved OSA outcomes versus sham (Guimaraes 2009). A myofunctional therapy meta-analysis (Camacho 2015) found pooled reductions in snoring and apnea-hypopnea index in selected populations. Those results support a daily airway routine as an adjunct for the mechanical snoring load - not as a substitute for GERD evaluation, PPI decisions, or CPAP when indicated.
A practical stack for many people with mixed reflux and snoring nights: STOP-BANG screen, clinician follow-up when scores or symptoms warrant testing, side sleep and bed elevation habits, alcohol timing, reflux medical care when appropriate, and a guided tongue/palate/throat routine so soft tissue holds better. Related guides: anti-snoring pillows and wedges, soft-palate drills, and oropharyngeal exercise studies.
Airway Trainer turns those drills into a short daily session so the tone half of a reflux-plus-snoring plan is not only willpower and YouTube tabs.
When to see a doctor first
Reading a comorbidity article is not a substitute for care. Get evaluated - do not only change dinner time - if you have:
- Gasping, choking, or witnessed pauses in breathing
- Severe daytime sleepiness or drowsy driving
- Chest pain, trouble swallowing, GI bleeding signs, or unintentional weight loss
- Heartburn needing frequent nonprescription medicine without a clinician plan
CPAP, oral appliances, positional therapy, GERD medicines, diet timing, bed elevation, weight management, nasal care, and airway exercises each solve different pieces. Match the tool to the cause after a real assessment when red flags are present.
Sources
- El Hage Chehade N, et al. J Gastroenterol Hepatol. 2023 Aug;38(8):1244-1251. PMID: 37300443.
Systematic review and meta-analysis (six studies, 2,950 patients): statistically significant association between GERD and OSA (OR 1.53, 95% CI 1.23-1.91). Association held across GERD and OSA diagnostic tools and after sensitivity checks for gender, BMI, smoking, and alcohol. GERD presence did not clearly change OSA severity metrics in the pooled analysis. - Wu ZH, et al. Sleep Breath. 2019 Jun;23(2):389-397. PMID: 29987514.
Meta-analysis of seven articles (2,699 patients): significant correlation between OSAHS and GERD (pooled OR 1.75, 95% CI 1.18-2.59) under a random-effects model with moderate heterogeneity. - Magliulo G, et al. Am J Otolaryngol. 2018 Nov-Dec;39(6):776-780. PMID: 30224217.
Literature review and meta-analysis of LPR in OSA: among 870 identified OSA patients, LPR incidence was about 45.2% (394 LPR+). AHI did not differ significantly by LPR status; mean BMI was higher in LPR+ patients. - Li C, et al. Sleep Breath. 2021. Effect of CPAP on gastroesophageal reflux in OSA: a meta-analysis. doi: 10.1007/s11325-020-02224-9.
Meta-analysis of CPAP in patients with OSA and reflux measures: CPAP was associated with reductions in percent time pH under 4, longest reflux duration, number of reflux events, DeMeester score, and reflux symptom scores; longer treatment windows showed clearer symptom improvement in subgroup analysis. - Tan X, et al. PeerJ. 2024 Apr 16;12:e17202. PMID: 38646475.
Systematic review and meta-analysis (22 studies): bidirectional links between sleep problems and GERD. Insomnia, sleep disturbance, and short sleep raised GERD odds; GERD raised odds of poor sleep quality, sleep disturbance, and short sleep duration. - Mayo Clinic. Gastroesophageal reflux disease (GERD): Symptoms and causes.
Patient-facing GERD overview: heartburn, regurgitation, lump-in-throat sensation; nighttime reflux can bring cough, laryngitis, and asthma-like symptoms. Lifestyle aggravators include late large meals, alcohol, and lying flat. - Mayo Clinic. Snoring: Symptoms and causes.
Clinical snoring overview: when snoring warrants evaluation and how lifestyle factors (including alcohol and sleep position) amplify airway vibration. - Mayo Clinic. Obstructive sleep apnea: Symptoms and causes.
OSA overview linking airway collapse with snoring, gasping, daytime sleepiness, and cardiovascular and metabolic risks that often co-travel with reflux phenotypes. - Ieto V, et al. Chest. 2015 Sep;148(3):683-691. PMID: 25950418.
Randomized trial: oropharyngeal (airway) exercises reduced snoring frequency and snoring power in habitual snorers - a non-reflux path to lower vibration load when tone is part of the problem. - Guimaraes KC, et al. Am J Respir Crit Care Med. 2009 May 15;179(10):962-968. PMID: 19234106.
Randomized trial: daily upper-airway exercises improved obstructive sleep apnea severity and snoring versus sham control. - Camacho M, et al. Sleep. 2015 May 1;38(5):669-675. PMID: 25348130.
Meta-analysis of myofunctional therapy for OSA: pooled trials show meaningful reductions in snoring and apnea-hypopnea index in selected populations.
GERD and snoring: FAQs
Does GERD cause snoring?
GERD and snoring often travel together, but reflux is rarely the only cause of snoring. Meta-analyses show a significant association between GERD and obstructive sleep apnea (for example OR about 1.53 and 1.75 in separate pooled analyses). Laryngopharyngeal reflux can inflame and swell throat tissues that vibrate and narrow during sleep. Still treat snoring as multi-factorial: anatomy, nasal blockage, alcohol, position, weight, and muscle tone all matter.
Can sleep apnea cause acid reflux?
Yes, that direction is part of the clinical story. Forceful breathing against a collapsed airway creates negative chest pressure that can favor reflux events. Sleep clinicians also describe a loop: apnea worsens reflux, and reflux-related swelling can worsen airway crowding. Treating OSA with CPAP has been associated with fewer reflux events in meta-analysis, which supports linked physiology rather than pure coincidence.
What is silent reflux (LPR) and how does it relate to snoring?
Laryngopharyngeal reflux is reflux that reaches the throat and voice box. Many people lack classic heartburn and instead report hoarseness, throat clearing, cough, mucus, or a lump-in-throat feeling. A meta-analysis of LPR in OSA found LPR in roughly 45% of identified OSA patients, without a clear AHI severity link. ENT demos emphasize looking for reflux changes when evaluating adult OSA and snoring.
Will treating heartburn stop my snoring?
Sometimes quieter nights follow better reflux control, earlier dinners, head-of-bed elevation, and less evening alcohol - especially when LPR-related swelling was an amplifier. It will not fix large tonsils, major jaw anatomy issues, or moderate-to-severe untreated OSA by itself. If snoring stays loud after lifestyle and medical reflux care, screen for sleep-disordered breathing rather than only raising PPI doses.
Does CPAP help GERD?
In people who have OSA plus reflux measures, pooled data suggest CPAP can reduce reflux event counts, acid exposure time, and some symptom scores. That is a reason to treat documented apnea seriously if both problems are present. CPAP is not a first-line GERD drug for people without OSA, and individual response still varies.
Can airway exercises help if reflux is part of my snoring?
Exercises target upper-airway muscle tone and snoring mechanics. Randomized trials (Ieto 2015, Guimaraes 2009) and a myofunctional therapy meta-analysis (Camacho 2015) support reductions in snoring and, in selected groups, apnea-hypopnea index. They do not neutralize acid or replace GERD evaluation. Use them as the tone half of a two-sided plan after red flags are screened.
When should I see a doctor about GERD and snoring?
Seek care for gasping, choking, witnessed apneas, severe sleepiness, chest pain, trouble swallowing, GI bleeding signs, unintentional weight loss, or heartburn that needs frequent nonprescription medicine. Do not self-diagnose nighttime choking as only reflux or only snoring. Bring partner reports and a simple food/alcohol/position log if you have one.
Quieter nights need both chemistry and tone
Screen and treat reflux and apnea when red flags show up. Airway Trainer handles the daily tongue, palate, and throat work that lowers snoring vibration load - the piece a PPI bottle cannot train for you.
Related reading: Alcohol and snoring · Best sleeping position · Snoring and vascular aging