aura6000 for sleep apnea
A third U.S. hypoglossal nerve stimulator story is now in the FDA + RCT lane - LivaNova aura6000 proximal continuous multi-contact stimulation, OSPREY randomized outcomes in Annals of Internal Medicine, and March 2026 PMA. Here is what differs from Inspire and Genio, and what still matters for residual snoring.


Quick answer
aura6000 is an FDA-approved (March 18, 2026 PMA) proximal hypoglossal nerve stimulator for selected adults with moderate-to-severe OSA who cannot use standard first-line options well. It uses a six-electrode proximal cuff and continuous stimulation aimed at holding upper-airway tone, rather than only breath-synced distal pulses. OSPREY did not require DISE and did not auto-exclude complete concentric collapse.
In the OSPREY RCT (Annals of Internal Medicine), 58.2% of active-therapy patients versus 13.5% of delayed-activation controls met the primary AHI responder definition at month 7, with median treatment AHI falling from 34.3 to 11.6 events per hour. ODI and sleepiness scores also favored active therapy. aura6000 is still surgery plus candidacy rules - not a mail-order snore gadget - and residual vibration can remain after AHI improves. Center availability and insurance rules still vary after PMA.
How aura6000 opens the airway
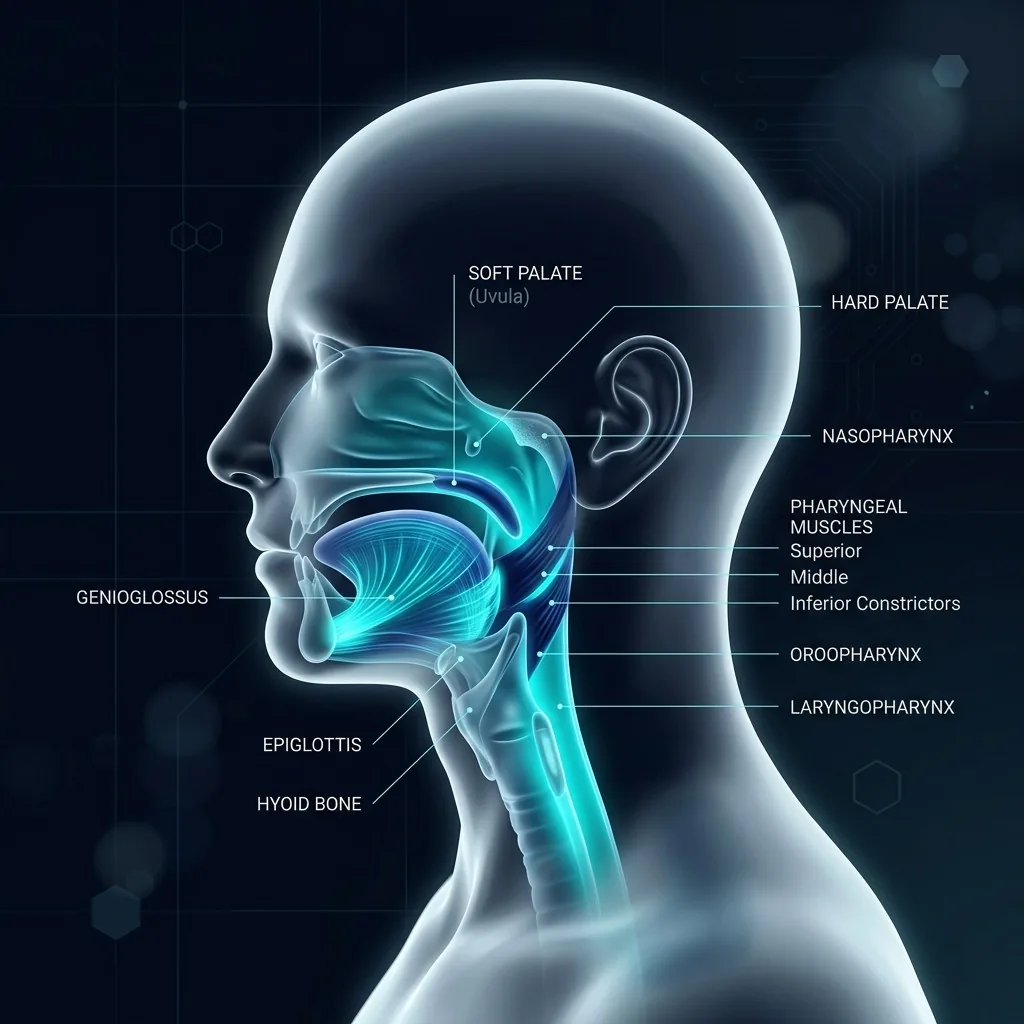
Obstructive sleep apnea is repeated upper-airway narrowing or collapse during sleep. When the tongue base and surrounding soft tissues lose tone, air cannot pass. Hypoglossal nerve stimulation (HGNS) is the electrical version of "keep the tongue and related openers online": branches of the nerve that control tongue shape and position get programmed stimulation so the airway stays more patent without a CPAP mask.
aura6000 is LivaNova's proximal multi-contact take on that idea. Houston Methodist otolaryngologist Omar Ahmed, an OSPREY site investigator, describes continuous stimulation that maintains tone across tongue and other pharyngeal structures, without a separate respiratory sensing lead. All 104 randomized OSPREY participants completed outpatient implantation (median about 72 minutes). Activation in the trial started about one month after implant for the early therapy arm.
Proximal nerve target, multi-contact cuff
Six electrodes on the proximal trunkUnlike distal cuff systems that hug selected hypoglossal branches farther forward, aura6000 places a multi-contact array more proximally so several electrode combinations can recruit tongue-protruding and stabilizing muscles. Company and trial materials emphasize selective activation of productive vectors rather than a single fixed stimulation pattern.
Continuous tone, not breath-by-breath pulses only
Steady airway support during sleepHouston Methodist trial investigators describe continuous proximal stimulation that maintains upper-airway muscle tone, aiming to stabilize tongue, soft palate, and pharyngeal walls. That differs from classic distal systems that deliver intermittent pulses timed to inspiration. Continuous does not mean "always comfortable at max settings" - titration still matters.
No respiratory sensing lead in the OSPREY design
Simpler implant stack on paperOSPREY materials highlight that pHGNS does not require a separate respiratory sensing lead to detect breathing. That can simplify surgery (median implant time about 72 minutes in OSPREY) but still leaves a fully implanted pulse generator and lead system that needs programming, charging/remote habits, and follow-up - not a mask-free miracle without clinic time.
CCC and DISE rules differ from older labels
Broader selection story, not automatic "anyone"OSPREY did not require drug-induced sleep endoscopy for enrollment and did not automatically exclude complete concentric collapse (CCC). Company communications after FDA PMA stress the absence of CCC contraindication/warning language that limited some earlier U.S. HGNS labels. Trial authors still caution that CCC-specific response depth needs more analysis - broader eligibility is not the same as equal response in every collapse pattern.
Tone and snoring can still remain
Implant is not a universal snore eraserHGNS treats collapsibility by electrically stiffening and advancing tongue-related structures. Soft-palate flutter, nasal blockage, alcohol, back sleep, and weak residual muscle tone can still leave vibration after AHI improves. Residual snoring plans still matter after activation.
What OSPREY and FDA approval showed
Two layers matter for patients reading late-2026 hospital explainers. First, the OSPREY randomized controlled trial published in Annals of Internal Medicine (online 21 April 2026; ClinicalTrials.gov NCT04950894). Second, FDA premarket approval of the aura6000 system on 18 March 2026 (PMA P250013), which rested on that clinical package.
| Layer | Population focus | Headline outcomes (summaries) |
|---|---|---|
| OSPREY RCT (Ann Intern Med) | n=104; moderate-to-severe OSA; 23 U.S. centers; PAP-intolerant pathway | M7 AHI responders 58.2% vs 13.5% control; ODI ≥25% drop 68.7% vs 37.8%; median AHI 34.3 to 11.6 (treatment); ESS 10 to 6 (treatment); sustained through M13 |
| FDA PMA (Mar 18, 2026) | Adults AHI 15-65; failed / intolerant / ineligible for standard options | Class III PMA P250013; company notes no CCC contraindication/warning language; commercial launch and next-gen MRI-compatible hardware still subject to center rollout and later supplements |
Numbers above are educational paraphrases of the Annals abstract, Houston Methodist trial coverage, FDA database materials, and LivaNova primary releases. Responder definitions, confidence intervals, adverse-event tables, reoperation rates, and full inclusion criteria belong in the peer-reviewed paper and PMA documents - not in a blog table alone.
Context from the broader treatment map: our 2026 treatment landscape page still owns the multi-option overview. Dedicated siblings cover Genio and residual training options. This page is the aura6000 / OSPREY owner so the branded proximal-HGNS query and November 2026 hospital news cycle have a single deep URL.
aura6000 vs Inspire vs Genio in plain English
Patients increasingly hear three implant brand names in the same consult. Mechanism videos (Mayo Clinic sleep medicine, Sengkang General Hospital ENT, NHS ENT surgeon Vik Veer on distal Inspire-style systems) still help for baseline HGNS literacy - then ask how proximal continuous multi-contact therapy changes the story.
| Topic | aura6000 (LivaNova) | Inspire (typical) | Genio (Nyxoah) |
|---|---|---|---|
| Stimulation style | Proximal multi-contact; continuous tone emphasis | Distal cuff; often breath-synced pulses | Bilateral under-chin paddles |
| Sensing lead | Not required in OSPREY design story | Respiratory sensing pathway common | External wearable power path; no chest IPG |
| CCC / DISE story | Trial did not require DISE; CCC not auto-excluded; label communications stress no CCC contraindication/warning | Historical U.S. pathways often used DISE and CCC restrictions | Separate ACCCESS program targeting CCC expansion after initial FDA lane |
| Pivotal evidence shape | OSPREY RCT with delayed-activation control | Longer real-world volume; STAR-era lineage | DREAM pivotal + ACCCESS CCC data |
| U.S. regulatory milestone | FDA PMA March 18, 2026 | Long-standing U.S. commercial HGNS path | FDA approval August 2025 |
Comparison points are educational summaries of trial reports, FDA materials, and clinician explainers - not a three-arm head-to-head randomized trial. Individual candidacy, insurance criteria, and surgeon experience dominate the choice.
Who these results apply to
Who labeled aura6000 use typically aims at
- Adults with moderate-to-severe OSA in the labeled AHI band (AHI 15-65 in FDA materials)
- People who failed, do not tolerate, or are ineligible for PAP, and who also meet criteria around oral appliances or pharmacotherapy as described on the label
- Candidates cleared after sleep medicine / sleep-surgery evaluation and medical fitness for outpatient implant
- Patients who can commit to device education, remote/charger habits, titration visits, and follow-up sleep testing when ordered
Who may need a different path
- Primary snoring without documented OSA, or mild OSA outside labeled criteria
- Central-predominant or mixed apnea patterns your team flags as poor obstructive-HGNS fit
- Medical, anatomic, or BMI exclusions your surgeon or sleep physician applies even if marketing language sounds broad
- Anyone expecting a weekend fix without diagnosis, implant candidacy workup, or post-op activation/titration
See a clinician first if...
- Gasping, choking, witnessed pauses, or severe daytime sleepiness
- You are already on CPAP, an oral appliance, oxygen, or prior upper-airway surgery and want to change therapy
- You are comparing Inspire, Genio, and aura6000: hardware and labeling differ; do not self-pick from ads alone
- Unexplained weight loss, chest pain, or other red-flag symptoms unrelated to elective implant planning
Practical next steps
Treat the Nov 2026 OSPREY wave as a consult prompt
Annals data (online April 2026) plus hospital explainers (Houston Methodist, Nov 4, 2026) and earlier FDA PMA (March 18, 2026) raise awareness. Commercial access, insurance criteria, and which centers offer aura6000 still vary. Start with a sleep diagnosis, then a team that actually implants and titrates HGNS.
Ask how proximal continuous stimulation differs from Inspire and Genio
Common consult points: continuous proximal multi-contact cuff vs distal unilateral cuff vs bilateral under-chin Genio paddles; sensing-lead needs; CCC and DISE policies on the label you are actually under; scar pattern; MRI notes on the currently approved generation vs next-gen supplements; real-world implant volume at that center.
Plan for activation delay, titration, and possible reoperation
OSPREY randomized therapy on at month 1 vs delayed control at month 7. Expect healing time, then programming. Houston Methodist notes some patients needed additional procedures such as reimplantation or explantation even without serious procedure-related adverse events in the abstract safety summary. Ask your center for their reoperation and explant rates.
Keep a residual-snoring stack
Even with a strong AHI response, soft-palate vibration, nasal blockage, alcohol timing, back sleep, and weak tone can keep nights loud. Positional habits, nasal care, prescribed PAP/oral appliances when still indicated, and oropharyngeal training cover different residual pieces.
This page is educational, not surgical advice. Hypoglossal nerve stimulation requires a licensed care team, candidacy testing, informed consent, and a plan for what happens to CPAP or oral appliances after activation. Do not stop prescribed therapy because a device headline looks encouraging.
Expert videos on aura6000, OSPREY, and HGNS
Clinician framing and demonstration context only. Clinical claims on this page are grounded in the Sources list, not in video captions. Prefer named ENT/sleep clinicians and primary trial discussants over pure manufacturer ads when learning mechanism trade-offs.
VJNeurology / OSPREY discussant - trial framing: randomized delayed-activation control, why RCT evidence matters next to older case-series HGNS history, no DISE requirement, and follow-on electrode reprogramming (PolySync) angles.
Jason (RPSGT) / TheLankyLefty27 - sleep-tech walkthrough of aura6000 booth claims, six-electrode proximal design versus classic Inspire-style systems, and how to read response-rate marketing carefully against PAP benchmarks.
Intervoke medical animation (pHGNS MOA) - short visual of proximal multi-contact targeting across tongue muscle groups. Treat as mechanism illustration, not outcome evidence.
Mayo Clinic Sleep Medicine - clinician podcast on HGNS realism: insurance and CPAP-failure definitions, candidacy friction, and why advertising is not the same as who actually qualifies.
Sengkang General Hospital ENT / sleep unit - hospital explainer of HGNS as a "pacemaker for the tongue," AHI band framing, DISE candidacy workflow for distal systems, and post-op expectations. Useful baseline literacy when comparing any implant brand.
When airway exercises still help
Hypoglossal implants move and stiffen tongue-related structures electrically. They do not automatically teach the soft palate and pharyngeal walls to hold tone every night for the rest of your life. If vibration remains after activation - or while you wait through candidacy, insurance, and healing - oropharyngeal training is the residual mechanical lever when a clinician says it is appropriate.
Randomized trials of oropharyngeal programs reduced snoring metrics (Ieto 2015) and improved OSA outcomes versus sham (Guimaraes 2009). A myofunctional therapy meta-analysis (Camacho 2015) found pooled reductions in snoring and apnea-hypopnea index in selected populations. Those results support a daily airway routine as an adjunct - not as a substitute for OSA diagnosis, PAP when indicated, or surgical implant pathways.
ENT education often notes that tongue-forward training shares a direction with HGNS design. A practical stack for many people exploring implants or living with residual snoring: STOP-BANG screen, sleep testing when scores or symptoms warrant it, prescribed PAP or oral appliance adherence until a surgeon restudies you, side-sleep habits, alcohol timing, and a guided tongue/palate/throat routine. Related guides: tongue exercises, soft-palate drills, Genio implant guide, and oropharyngeal exercise studies.
Airway Trainer turns those drills into a short daily session so residual vibration work is not only willpower and random YouTube tabs while implant candidacy or titration runs in parallel.
When to see a doctor first
A news cycle about a new implant is not a care plan. Get evaluated - do not only screenshot a trial table - if you have:
- Gasping, choking, witnessed pauses, or severe daytime sleepiness
- Drowsy driving or work impairment from sleepiness
- Existing CPAP, oral appliance, oxygen, or prior airway surgery you want to change
- Interest in HGNS: you need formal candidacy testing, not a product page alone
CPAP, oral appliances, hypoglossal nerve stimulation (Inspire, Genio, or aura6000 when you qualify and a center offers it), positional therapy, nasal surgery, weight management, and airway exercises each solve different pieces. Match the tool to the cause after a real assessment.
Sources
- Malhotra A, Schwartz AR, Lovett EG, et al.; OSPREY Investigators. Proximal hypoglossal nerve stimulation for obstructive sleep apnea in the OSPREY study: a randomized controlled trial. Ann Intern Med. 2026;179(6):812. Epub 2026 Apr 21. doi: 10.7326/ANNALS-25-04414. ClinicalTrials.gov: NCT04950894.
Primary peer-reviewed OSPREY RCT of proximal hypoglossal nerve stimulation (pHGNS) in 104 adults with moderate-to-severe OSA at 23 U.S. centers: month-7 AHI responder rate 58.2% (active) vs 13.5% (control), ODI response 68.7% vs 37.8%, ESS improved in treatment only, no serious procedure-related adverse events reported in the abstract. Use the full Annals paper for estimands, safety tables, and limitations (unblinded, small sample, short follow-up). - Houston Methodist Leading Medicine Blog. OSPREY trial demonstrates promise of new proximal hypoglossal nerve stimulator for sleep apnea. Omar Ahmed, MD. November 4, 2026.
Named academic center explainer of OSPREY: continuous six-electrode proximal stimulation (vs breath-synced distal systems), no respiratory sensing lead, median 72-minute outpatient implant, CCC not automatically excluded, DISE not required for trial selection, median AHI 34.3 to 11.6 at seven months, benefits through 13 months, and candidacy caveats that CCC subgroup responses still need deeper analysis. Notes the device was not routine clinical care at Houston Methodist at publication time. - LivaNova PLC. LivaNova receives U.S. FDA premarket approval for aura6000 System to treat moderate to severe obstructive sleep apnea. Business Wire / investor release, March 19, 2026 (decision date March 18, 2026; PMA P250013).
Company primary announcement of FDA PMA for the aura6000 system, describing proximal HGNS, OSPREY as the pivotal evidence base, and company claims that the approval lacks complete concentric collapse contraindication or warning language used on some earlier U.S. HGNS labels. Also notes next-generation MRI-compatible plans subject to later FDA supplement review and commercial launch timing. - U.S. Food and Drug Administration. Premarket Approval database and approval order summary for aura6000 system (P250013). Decision date March 18, 2026. Applicant: LivaNova USA, Inc. Product code MNQ.
Regulatory primary source for labeled indication (adult moderate-to-severe OSA, AHI 15-65; failed, intolerant of, or ineligible for PAP, oral appliances, or pharmacotherapy), PAP failure/intolerance definitions, system components, and post-approval study obligations including extended OSPREY follow-up. - Mayo Clinic. Obstructive sleep apnea: Diagnosis and treatment.
Patient-facing overview of OSA evaluation and standard options (CPAP, oral appliances, lifestyle, surgery) and why device choice depends on phenotype, tolerance, and clinician assessment. - Mayo Clinic. Snoring: Diagnosis and treatment.
Clinical snoring overview: when snoring warrants apnea evaluation, and that anatomy and muscle tone still matter after any device or lifestyle change. - Ieto V, et al. Chest. 2015 Sep;148(3):683-691. PMID: 25950418.
Randomized trial: oropharyngeal (airway) exercises reduced snoring frequency and snoring power in habitual snorers - a non-implant path when residual vibration or mild tone problems remain. - Guimaraes KC, et al. Am J Respir Crit Care Med. 2009 May 15;179(10):962-968. PMID: 19234106.
Randomized trial: daily upper-airway exercises improved obstructive sleep apnea severity and snoring versus sham control. - Camacho M, et al. Sleep. 2015 May 1;38(5):669-675. PMID: 25348130.
Meta-analysis of myofunctional therapy for OSA: pooled trials show meaningful reductions in snoring and apnea-hypopnea index in selected populations.
aura6000 and sleep apnea: FAQs
What is the aura6000 system for sleep apnea?
aura6000 (LivaNova) is an implantable proximal hypoglossal nerve stimulation (pHGNS) system for selected adults with moderate-to-severe obstructive sleep apnea who cannot use standard first-line options successfully. A multi-contact electrode array on a more proximal segment of the hypoglossal nerve delivers continuous stimulation intended to keep tongue and related upper-airway muscles from collapsing during sleep. Power and control come from an implanted pulse generator with clinician programming and a patient remote/charger pathway.
Is aura6000 FDA approved in the United States?
Yes. FDA granted premarket approval (PMA P250013) with a decision date of March 18, 2026 for adults with moderate-to-severe OSA (AHI 15-65) who failed, do not tolerate, or are ineligible for standard-of-care options such as PAP, oral appliances, or pharmacotherapy, per FDA and company materials. Approval does not mean every center offers it yet, and next-generation hardware (for example MRI-compatible updates described by the company) may still depend on later supplements and commercial rollout timing.
What did the OSPREY trial show?
OSPREY randomized 104 implanted adults 2:1 to earlier active therapy versus delayed activation. At month 7, 58.2% of the treatment arm versus 13.5% of controls met the primary AHI responder definition (at least 50% AHI reduction and AHI below 20). ODI improved by at least 25% in 68.7% versus 37.8%. Median treatment-arm AHI fell from 34.3 to 11.6 events per hour. ESS improved in the active arm. Benefits were described as sustained through month 13. Limitations include lack of blinding, modest sample size, and relatively short follow-up in the primary report.
How does aura6000 differ from Inspire and Genio?
All three are hypoglossal nerve stimulation families for selected OSA, but hardware and trial stories differ. Typical Inspire systems use a distal cuff with breath-synced stimulation and a chest generator. Genio uses a leadless bilateral under-chin implant with an external nightly power patch. aura6000 uses proximal multi-contact continuous stimulation without a respiratory sensing lead in the OSPREY design story, and its U.S. label communications emphasize no CCC contraindication/warning language that limited some earlier HGNS labels. None is automatically best for every anatomy; surgeon experience and phenotype dominate.
Do I still need drug-induced sleep endoscopy (DISE) for aura6000?
OSPREY did not require DISE for trial enrollment, and company/FDA communications highlight broader selection than older CCC-restricted pathways. Individual centers may still use endoscopy or imaging when it changes surgical planning. Ask the implanting team what workup they actually require for insurance and safety, not only what the trial allowed.
Does aura6000 cure snoring?
No implant is framed as a universal snore cure. OSPREY targeted breathing-event rates, oxygenation, and patient-reported outcomes in selected OSA. Residual soft-palate flutter, nasal issues, alcohol, position, and weak muscle tone can still produce sound after AHI improves. Ask your team what residual snoring plan they use after activation.
Can airway exercises help if I am considering or recovering from HGNS?
Exercises do not replace implant candidacy workups or prescribed OSA therapy. Randomized oropharyngeal programs (Ieto 2015, Guimaraes 2009) and a myofunctional therapy meta-analysis (Camacho 2015) support lower snoring load and, in selected groups, better AHI as an adjunct. ENT education often notes that tongue-forward training shares a mechanical direction with hypoglossal stimulation. Use exercises only when your clinician says they fit your stage of care.
Implants move the tongue. Tone still needs reps.
Follow clinician-led OSA and surgical care when you qualify for HGNS. Airway Trainer handles the daily tongue, palate, and throat work that lowers residual snoring vibration - the piece an implant cannot train for you.
Related reading: Genio sleep apnea implant · New sleep apnea treatments 2026 · CPAP 4-hour rule